Blog
Understanding Frontotemporal Dementia
Published
Updated
Written by Lee Grunberg, M.B.A. — President & CEO
Reviewed by Bethel McMaster, BScN, RN — Director of Business Development

On this page13 sections
Key Takeaways
- Frontotemporal dementia (FTD), also called frontal lobe dementia, affects the parts of the brain that guide behaviour, personality and language.
- The first changes are usually in behaviour or speech rather than memory, which is why FTD can be mistaken for stress, depression or another mental health condition.
- FTD most often begins between the ages of 45 and 65, earlier than most Alzheimer’s disease, and it is the second most common cause of dementia in people under 65.
- In Ontario, diagnosis usually starts with the family doctor and a referral to a specialist such as a neurologist, geriatric psychiatrist, or memory clinic.
- The 7 stages of frontotemporal dementia are a general guide. Each person moves through the illness at their own pace.
- Integracare’s Caregivers are trained in dementia care through our partnership with the Alzheimer Society of Toronto, and every care plan is overseen by a Registered Nursing Coordinator.
Frontotemporal dementia often shows itself first through changes in personality, behaviour or language rather than memory. Someone who was always thoughtful may become blunt or impulsive, lose interest in hobbies and friends, or have trouble finding the right words. Because these changes often begin between the ages of 45 and 65, Families and even doctors may first put them down to stress, depression or a difficult stage of life.
Frontotemporal dementia, or FTD, is less common than Alzheimer’s disease, but it is the second most common cause of dementia in people younger than 65. The changes it brings are different from the memory loss most people expect with dementia, and different again from other common types of dementia, such as Lewy body dementia and vascular dementia.
At Integracare, our Caregivers are educated in dementia care through our partnership with the Alzheimer Society of Toronto, which began in 2017. That training covers how each type of dementia affects a person, so care can be adapted to your loved one’s diagnosis. With FTD, that often means patience with changes in behaviour and communication rather than a focus on memory.
Bringing in dementia-trained support early, while your loved one can still share their preferences, gives them a say in how they are cared for. A Caregiver who spends time with your loved one each week also comes to know their routines and can share changes in behaviour, or in how they respond to a new medication, with the Registered Nursing Coordinator who oversees their care and with your Family.
Writing down what you notice, and roughly when it started, gives your loved one’s doctor a clearer picture and is a useful first step for your Family.
Is Frontal Lobe Dementia the Same as Frontotemporal Dementia?
Yes. If you have been reading about your loved one’s symptoms, or have heard different terms from different doctors, the names can be confusing. Frontal lobe dementia, frontotemporal lobe dementia, and frontotemporal dementia all describe the same group of conditions. You may also come across Pick’s disease, an older name that today usually refers to one specific form of FTD.
In Canada, doctors and the Alzheimer Society of Canada use frontotemporal dementia, or FTD, so that is the name you are most likely to see on referral letters and in the support resources available to your Family.
What Is Frontotemporal Dementia?
FTD is a group of conditions in which nerve cells in the brain’s frontal lobes (behind the forehead) and temporal lobes (behind the ears) are gradually damaged.
The frontal lobes help with planning, judgement, motivation, self-control, and understanding social situations.
The temporal lobes help with language, understanding the meaning of words, recognizing faces and objects, and processing emotions.
Which symptoms appear first depends on which area is affected first. In most people with FTD, abnormal proteins, most often tau or TDP-43, build up in these parts of the brain.
The Main Types of Frontotemporal Dementia
- Behaviour-led FTD (behavioural variant FTD, or bvFTD): the most common form. It mainly changes personality, behaviour, and judgement, such as loss of inhibition, apathy, less concern for others, compulsive habits, and changes in eating.
- Language-led FTD (primary progressive aphasia, or PPA): these forms affect speech and language first. In the semantic variant, a person gradually loses the meaning of words and may ask what everyday words mean. In the non-fluent (agrammatic) variant, speech becomes slow and effortful, and sentences lose their grammar.
- Movement-related forms: some people develop stiffness, slowness, balance problems, or muscle weakness. Related conditions include progressive supranuclear palsy and corticobasal syndrome, and a smaller number of people develop ALS alongside FTD.
The types often overlap as the illness progresses, so someone who starts with language changes may later have behaviour changes too.
At What Age Does Frontotemporal Dementia Start?
FTD most often begins between the ages of 45 and 65, although it can start earlier or later. Alzheimer’s disease usually begins after 65. Because FTD tends to arrive while people are still working, driving, and managing their own finances, it helps to plan early for those parts of life.
| Feature | Frontotemporal dementia | Alzheimer’s disease |
|---|---|---|
| Typical age when symptoms begin | Most often 45 to 65 | Usually after 65 |
| First changes | Behaviour, personality or language | Memory, especially recent events |
| Memory in the early stage | Often relatively unaffected | Usually affected early |
| Often first mistaken for | Stress, depression or a mental health condition | Normal aging |
What Causes Frontotemporal Dementia?
In most cases, the cause of FTD is not known. Genetics plays a larger role in FTD than in most other types of dementia. Roughly 4 in 10 people with FTD have a family history of dementia or a related condition, and about 1 in 5 have a clear inherited pattern, most often linked to changes in the GRN, MAPT, or C9orf72 genes.
If FTD runs in your Family, ask the doctor about a referral to a genetic counsellor, who can explain what testing involves and what the results would mean for relatives.
Frontotemporal Dementia: Signs and Symptoms
As with the other most common types of dementia, FTD symptoms vary from person to person. They generally fall into three groups: changes in behaviour and personality, changes in language, and changes in movement. Behaviour changes are the most common first sign. Because they can look like a mental health concern, FTD is sometimes first diagnosed as depression, bipolar disorder, or another psychiatric condition.
Frontotemporal dementia symptoms may include behaviours such as:
- Obsessive or compulsive actions.
- Apathy or reclusiveness.
- Decreased motivation.
- Mood changes, which can be sudden.
- Loss of inhibition leading to inappropriate social behaviours.
- Outbursts of laughter or tears.
- Stunted emotions.
- Reduced judgement.
- Indifference to personal hygiene.
- Changes in eating, such as overeating, a new craving for sweets, or eating non-food items.
- Less empathy for others, such as seeming unmoved when someone is upset.
People living with the language-led forms of FTD, known as primary progressive aphasia, may notice changes in communication first.
Frontotemporal dementia symptoms that relate to communication may present as such:
- Struggling to find words.
- Misunderstanding the meaning of words.
- Increasing inability to read or write.
- Stuttering.
- Speaking less, or not at all.
- Making sounds instead of forming words.
- Speaking slowly.
Symptoms of frontotemporal dementia may also include challenges with motor skills. Movement changes in FTD can look like those seen in Parkinson's and may include:
- Tremors.
- Balance and coordination challenges.
- Muscle twitches or spasms.
- Trouble swallowing.
The 7 Stages of Frontotemporal Dementia
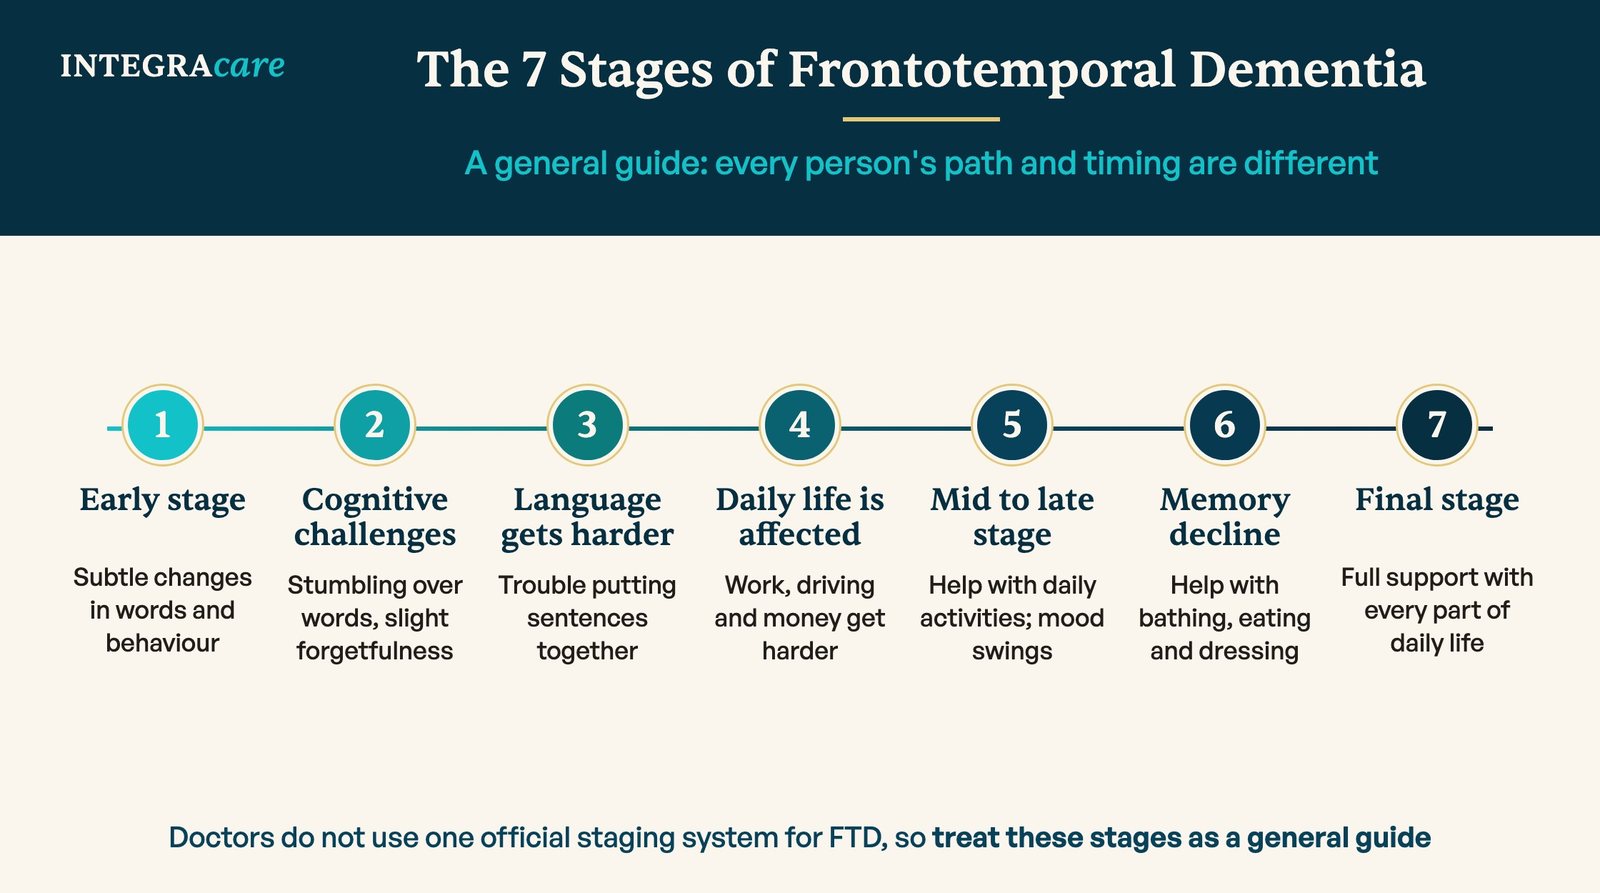
FTD is a progressive illness, which means symptoms change and increase over time. The 7 stages of frontotemporal dementia below describe how the illness commonly progresses. Doctors do not use one official staging system for FTD, so treat these stages as a general guide rather than a timeline.
Symptoms will vary between individuals, as will the timeline and the progression of dementia symptoms. Some may stall at one stage for many years, while others will quickly move through the seven stages.
1. Early Stage:
Changes are subtle at this stage, and FTD is rarely diagnosed yet. Your loved one may have occasional trouble finding words or act in ways that seem out of character, such as making a tactless remark or losing interest in plans they used to enjoy. Families often put these changes down to stress or mood, and it can be hard to tell at first that an illness is behind them.
2. Cognitive Challenges:
In the second stage of frontotemporal dementia, people may still only show mild symptoms, including stumbling over words, struggling to put together a sentence, and slight forgetfulness. From an outsider’s perspective, these changes may be attributed to age or poor memory; however, those close to the individual may begin to worry.
3. Heightened Difficulty with Language:
At stage three of frontotemporal dementia, one of the middle stages, people living with the illness may experience consistent challenges with their language skills, including struggling to piece together sentences and remembering words or terminology. Poor tact and a decline in their motivation, partnered with reduced social etiquette, can often cause challenges in their workplace or during social gatherings.
4. Day-to-Day Life Is Affected:
As FTD moves into stage four, more complex language becomes harder, and memory changes seen in other types of dementia may start to appear. Changes in language and behaviour begin to affect everyday life, such as keeping up with work, driving, managing money, or staying in touch with friends.
Your loved one may not recognize these changes in themselves. This is a common part of FTD, and it can make conversations about getting help harder for the whole Family. Offering help with specific tasks, such as meals, appointments, or errands, often feels easier to accept than a conversation about care.
This is often the stage when Families bring in support for a few hours a week. We are happy to talk through what you are seeing, or to arrange a free in-home assessment where our care team learns about your loved one and the support your Family needs.
Stage 5: Mid to Late Stage
In the mid to late stages of FTD, your loved one may struggle to make decisions while experiencing further difficulties with language and memory impairment. For this reason, it’s at this stage that help may be needed with some Activities of Daily Living (ADLs).
The most noticeable symptoms at this stage are changes in behaviour, including frequent mood swings and larger personality changes than in the earlier stages.
6. Memory Decline
Memory loss becomes more noticeable in stage six, and symptoms can start to look more like Alzheimer’s disease. Your loved one may become quieter and more withdrawn, and may have balance problems, stiffness, or tremors.
Everyday tasks such as bathing, eating, and dressing now usually need a helping hand, and some Families arrange 24-hour home care so someone is always there. A Personal Support Worker (PSW) can help with these daily tasks with patience and respect. We take care to match each Caregiver with your loved one, looking at their needs, abilities, and the things they enjoy.
7. The Final Stage of Frontotemporal Dementia
In the final stage, your loved one will need full support with every part of daily life and may have difficulty speaking, moving, and swallowing. FTD is a life-limiting illness, and complications such as pneumonia, often linked to swallowing problems, or a serious fall can occur at this stage. Palliative care at home focuses on comfort and on supporting your Family through this time.
How Frontotemporal Dementia Is Diagnosed in Ontario
There is no single test for FTD. In Ontario, diagnosis usually follows these steps:
- Start with the family doctor. Describe the changes you have noticed and when they began. Your notes matter here, because your loved one may not see the changes themselves.
- Rule out other causes. The doctor may check thinking and memory, order blood work, and arrange a brain scan such as a CT or MRI.
- See a specialist. This is often a neurologist, geriatric psychiatrist, geriatrician, or memory clinic. Specialists may do detailed thinking and language testing and sometimes further imaging.
- Ask about genetic counselling if FTD or a related condition runs in the Family.
Reaching an FTD diagnosis can take time, partly because early symptoms can look like a mental health condition. If something still does not seem right, it is reasonable to ask for a second opinion or a referral to a specialist with FTD experience.
After a diagnosis, ask the doctor for a referral to the Alzheimer Society’s First Link program, which connects Families with education and local support. You can also contact Ontario Health atHome at 1-833-515-1234 to ask about publicly funded home care.
Caring for Someone With Frontotemporal Dementia at Home
Caring for someone with FTD often means adjusting to changes in personality as much as changes in ability. Your loved one is still the same person, and the changes you see come from the illness, not from a choice they are making. Responding calmly, rather than correcting or arguing, usually works better for both of you.
These practical steps can make daily life at home easier:
- Keep a steady routine. Regular times for meals, outings, and rest reduce frustration and help your loved one know what comes next.
- Respond to the feeling behind the words. If a comment is hurtful or a request is unreasonable, gently moving on to another activity often works better than explaining why it was wrong.
- Plan around changes in eating. Serve meals at regular times, keep sweets and snacks out of sight, and put cleaning products and other non-food items away.
- Protect finances early. Impulsive spending and poor judgement with money are common in behavioural variant FTD. Set up powers of attorney for property and personal care while your loved one can still take part in those decisions, and ask the bank about limits on cards and accounts.
- Make the home safer. Clear tripping hazards, keep familiar furniture in place so the space still feels like home, and add equipment such as grab bars, a bath seat, or a hospital bed as mobility changes. Integracare can help your Family arrange equipment such as bath seats, Hoyer lifts, and hospital beds.
- Plan for the hours you are away. If your loved one is home alone while you work, think about which times of day are hardest, such as mealtimes or late afternoon, and arrange support for those hours first.
Agitation, repeated questions and restlessness are known as responsive behaviours, and there are practical ways to respond to personality changes and responsive behaviours that can make those moments calmer.
Your own rest matters too. Respite care gives you a few hours, a night or a few days away while your loved one is cared for at home.
Frontotemporal Dementia Treatment
There is no cure for FTD, and no medication has been approved to slow it. Treatment focuses on easing symptoms and supporting daily life.
Medications for behaviour: Doctors sometimes prescribe antidepressants called SSRIs, or trazodone, to help with symptoms such as irritability, compulsive behaviour, or agitation.
Alzheimer’s medications: Drugs commonly used for Alzheimer’s disease are generally not recommended for FTD and can make some behaviour symptoms worse, so ask the doctor about any medication your loved one is offered.
Speech-language therapy: A speech-language pathologist can help someone with primary progressive aphasia use communication aids and strategies for as long as possible.
Physiotherapy and occupational therapy: These can help with balance, movement, and safety at home as physical symptoms develop.
Everyday activities matter too. Gardening, short walks, chair exercises, music your loved one has always enjoyed, and simple art or puzzles can give the day structure and enjoyment. Choose activities that match what your loved one can do now.
When you talk with your loved one, speak slowly and clearly, keep sentences short, and allow time for a reply. Pictures, gestures, and familiar objects can help when words are hard to find.
When to Bring In Dementia-Trained Support
It may be time to add support when your loved one can no longer be left alone safely, when behaviour changes are hard to manage on your own, or when your own sleep, work, or health is suffering. Starting with a few hours a week while things are manageable gives your loved one time to get to know a Caregiver before more help is needed.
When you compare dementia care at home, ask:
What dementia training do your Caregivers receive, and does it cover responsive behaviours and communication?
Who oversees the care plan, and is a nurse involved?
How do you match Caregivers with Clients, and how do you keep the same Caregivers in place?
Can care increase to overnight, live-in, or 24-hour support as needs change?
If your loved one is in the middle stages, consider whether someone with mid-stage dementia can stay at home and what support that would involve.

Dementia Care at Home With Integracare
Integracare has supported Families with dementia care at home for more than 30 years, and today we provide care in Toronto, Mississauga, Ottawa, and Winnipeg. Through our partnership with the Alzheimer Society of Toronto, which began in 2017 and was renewed in 2026, our Caregivers take the Society’s professional dementia courses, including U-First! and Gentle Persuasive Approaches, which focus on understanding and responding to changes in behaviour.
Every care plan is overseen by a Registered Nursing Coordinator and changes as your loved one’s needs change, and a nurse is available 24/7. Each Caregiver is carefully matched to the Client, and we keep the same Caregivers with your loved one wherever possible. Our dementia home care can start with a few hours a week and grow to overnight, live-in, or 24-hour care.
During a free in-home assessment, our care team learns how FTD is affecting your loved one’s day, what still brings them enjoyment, and where your Family needs the most help, then puts together a care plan with you.
Frequently Asked Questions About Frontotemporal Dementia
How is frontotemporal dementia diagnosed?
There is no single test. A doctor will usually take a detailed history from your loved one and the Family, check thinking and language, order blood work and a brain scan, and refer to a specialist. Most people receive a diagnosis based on symptoms and scans. In inherited cases, genetic testing can confirm FTD.
What are the first signs of frontotemporal dementia?
Early signs are usually changes in behaviour or language rather than memory:
- Apathy or loss of interest and motivation.
- Loss of inhibition, tactless or inappropriate comments.
- Compulsive or repetitive behaviours.
- Trouble planning or finishing tasks.
- Changes in eating, such as overeating, craving sweets or eating non-food items.
- Trouble finding words or understanding what words mean.
Does frontotemporal dementia affect memory?
Not usually at first. In the early stages, memory and awareness of time are often relatively unaffected, which is one way FTD differs from Alzheimer’s disease. Confusion and forgetfulness tend to appear in the later stages.
How fast does frontotemporal dementia progress?
The pace varies widely. Some people stay at one stage for years, while others change more quickly. Over time, most people lose some ability to speak, understand others, and manage their own behaviour, and need more help with daily activities. A care plan that is reviewed regularly lets support increase as needs change.
What is the life expectancy with frontotemporal dementia?
It varies a great deal. Research suggests people live on average about 7 to 9 years after symptoms begin, and some live much longer. Age, the type of FTD, and whether movement symptoms develop all play a part. Your loved one’s specialist can give a better sense of what to expect.
Can someone with frontotemporal dementia stay at home?
Often, yes, with the right support. People with FTD can stay at home through the early and middle stages with help from Family and Caregivers, and some stay through the later stages with live-in or 24-hour care and nursing oversight. Whether home is the right choice depends on safety, behaviour changes and the support your Family can arrange.
What should I look for in a Caregiver for someone with frontotemporal dementia?
Look for dementia training that covers responsive behaviours and communication, not only memory loss, along with a calm and patient manner. Ask whether a nurse oversees the care plan, how Caregivers are matched to Clients and how the agency keeps the same Caregivers in place, since familiar people and routines matter in FTD.
What support is available in Ontario for Families caring for someone with FTD?
Ask the doctor for a referral to the Alzheimer Society’s First Link program, which connects Families with education and local support. Ontario Health atHome (1-833-515-1234) assesses for publicly funded home care. Private home care can add hours, overnight support, or respite, and support groups for young-onset dementia can connect you with Families in a similar situation.
Free In-Home Assessment
The Care Your Family Deserves Starts Here
Speak with our team about a personalized care plan. Book a free, no-obligation in-home assessment and we will help you find the right support for your loved one.
About the Author: Lee Grunberg

President & CEO, M.B.A.
Lee joined Integracare as President & CEO on August 2, 2016 after an approximately 20 year career in Private Equity and Investment Banking. Lee brings tremendous operational knowledge and governance experience along with an incredible passion and energy to Integracare.